
Mothers knelt in a Vienna hospital, wringing their hands, and begged to change wards. They had landed in the First Clinic, run by doctors and medical students. In 1842, nearly sixteen percent of the mothers who gave birth there died, about one in six. In the Second Clinic, in the same hospital, the midwives lost under eight percent. Across six years it was ten percent against four (Figure 1).
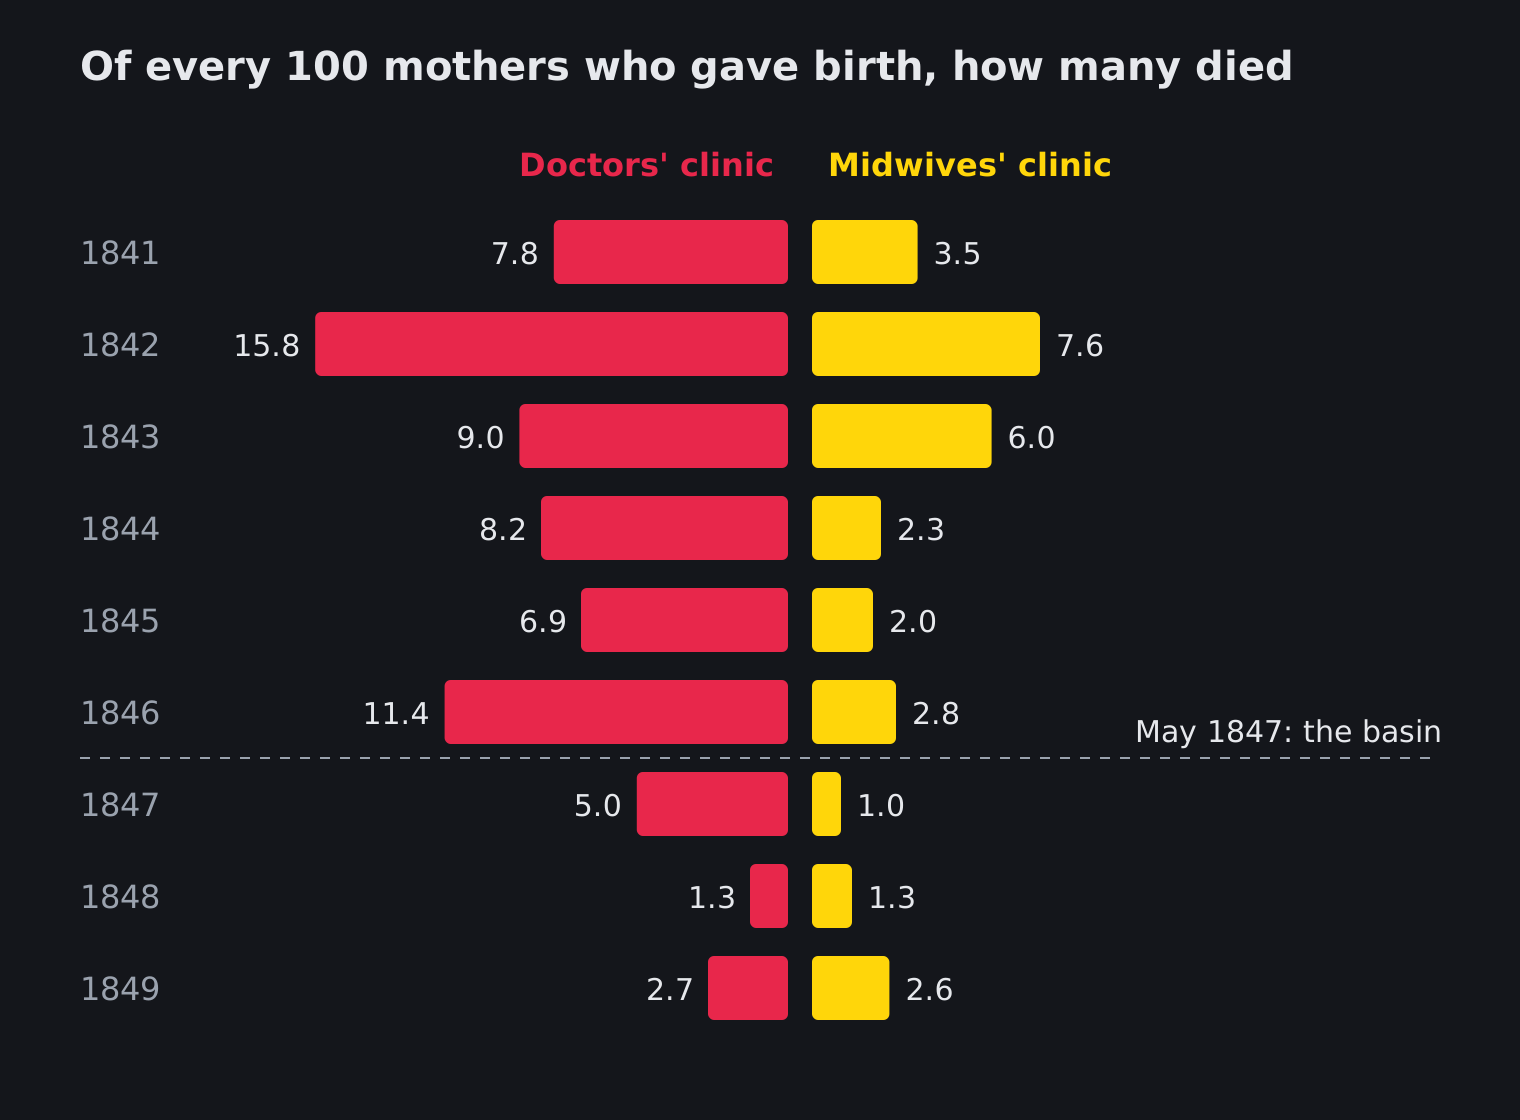
Figure 1. The two clinics back to back, one row a year, counting how many of every 100 mothers died. The doctors’ bar is longer every year until the basin, then the two match. From the yearly tables in Semmelweis (1861); 1841 to 1846 are the rows of Figure 4. Drawn for this piece.
A young doctor in the First Clinic, Ignaz Semmelweis, set out to learn what was killing the mothers. Both clinics stood inside the city’s great general hospital, long wings of red-roofed wards set around garden courtyards (Figure 2). Since 1998 those wings have been a campus of the University of Vienna, with university institutes in the old wards and restaurant tables outside (University of Vienna).
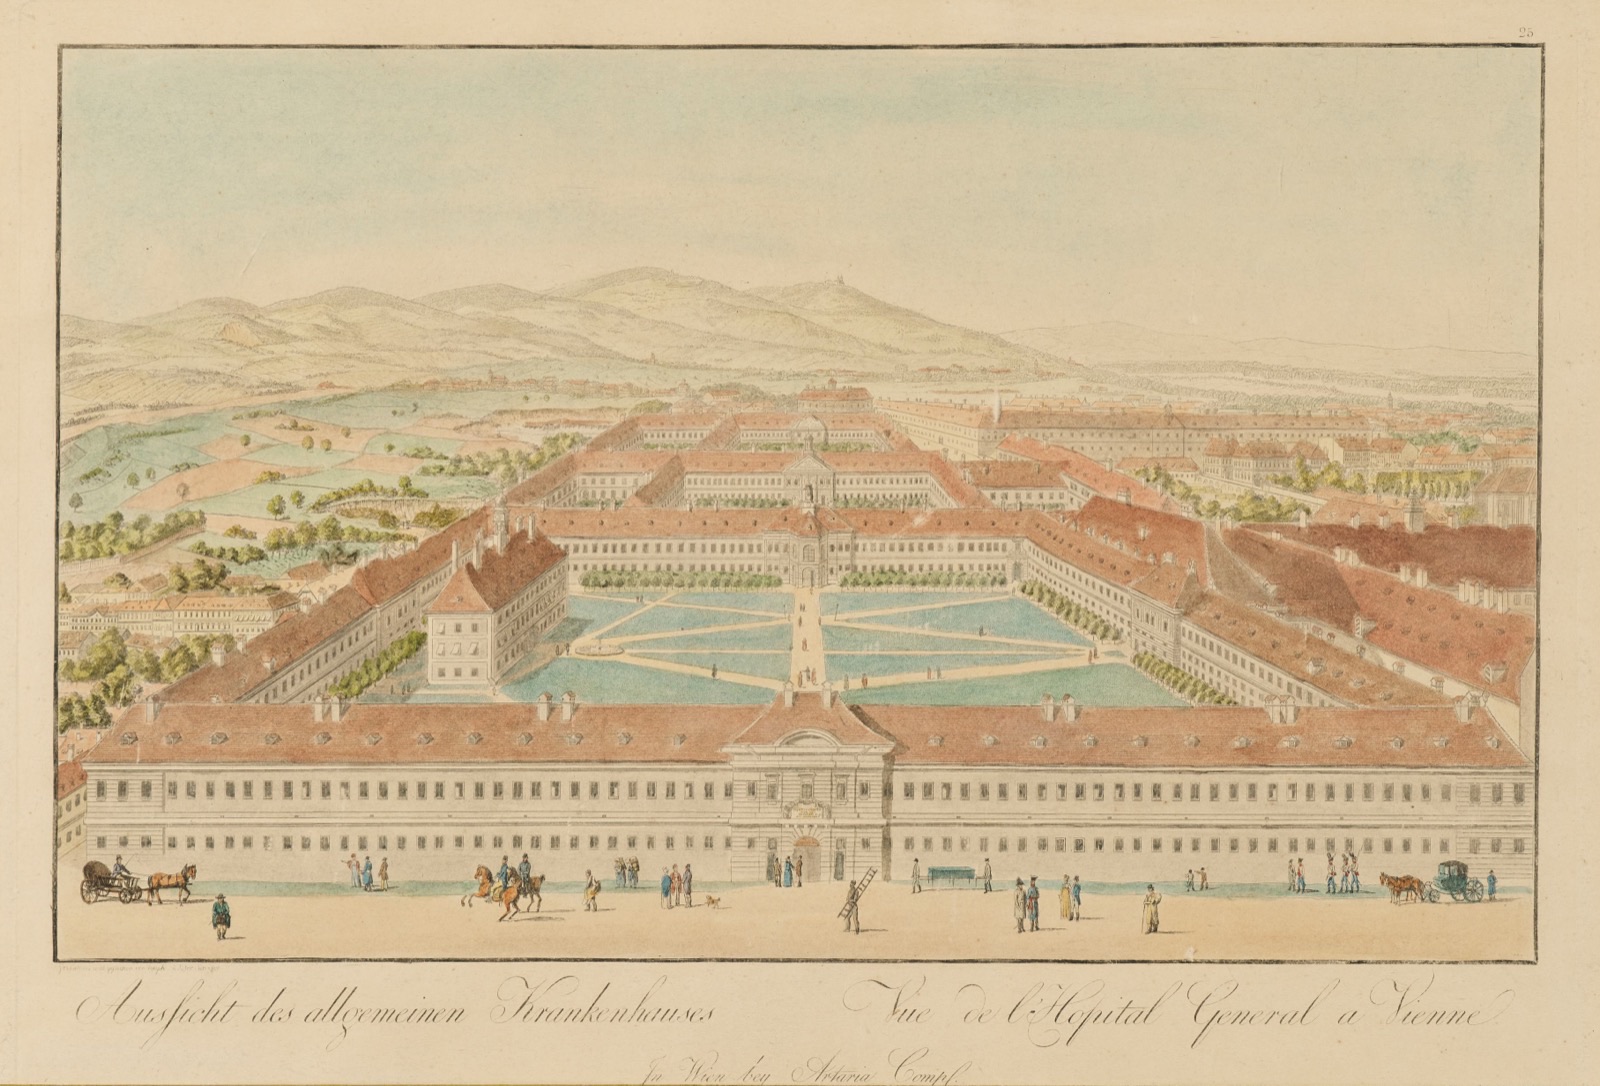
Figure 2. The Vienna General Hospital about 1784, the year it opened, decades before the two clinics. Hand-colored engraving by Josef and Peter Schaffer, public domain, via Wikimedia Commons.

His first guess was posture. The midwives’ mothers gave birth on their sides, the doctors’ mothers on their backs. He asked the doctors to switch. The death rate stayed the same.
His second guess was fear. After a mother died, a priest walked through the doctors’ ward ringing a bell. Semmelweis proposed that mothers were falling sick and dying of fear at the sound. Even after the priest stopped ringing the bell, the clinic’s numbers did not improve.
Then a scalpel slipped. His friend Jakob Kolletschka, a professor, died in 1847 after a student’s scalpel cut Kolletschka’s finger during an autopsy. Kolletschka’s own autopsy showed the signs Semmelweis had seen in mothers who died of childbed fever, an infection after giving birth. The doctors often did autopsies before delivering a baby, and they did not properly clean their hands in between. He called what they carried “cadaverous particles.” He set out a basin of chlorinated lime, a bleaching powder in water, and ordered every doctor to wash in it before examining a mother. In 1848, deaths in the doctors’ clinic fell to 1.27 percent, below the midwives’ 1.33. The number settled what was killing the mothers. It did not settle whether anyone would believe him.
You probably run a posture guess of your own. Say you plan to walk every morning, and every time the plan dies by the second week. Months ago you said out loud, “I am not a morning person,” and set a second alarm. Two weeks later the shoes are back by the door, and the friend at the corner waits alone. Not a morning person was the first reason within reach, and you never changed one thing alone to test it. How do you tell a guess from a cause before it costs you another fourteen mornings?
Semmelweis’s search found a mechanism, a chain of causes that predicts what happens next. A mechanism works like a loose wire behind a flickering lamp: find the wire, and every flicker makes sense. His life after the chlorine ran into questions with no mechanism to find.
Most people carry a few questions like that, about work, family or what they owe. Five from a list of twelve favorite questions ask what he should do after 1848, once he was right and Vienna would not listen.
What the Hands Carried
Under the same roof as the bell, more of the midwives’ mothers lived. Read each clinic as a system, with the three things the systems thinker Donella Meadows looked for: its parts, what pushes what, and what the whole is for. Read that way, the two nearly match (Figure 3).
Figure 3. Two clinics read as one system
Both had one purpose. The parts differed in three places: how the mothers lay, the bell, and the autopsies. Russell Ackoff’s test takes one part out of a system and watches what the whole can still do. It works like pulling one plug from a power strip to see what stops. The Second Clinic ran that test every day, but with three parts changed at once, so it could not say which one mattered.
Everyone on the ward carried a mental model, a set of assumptions about a system: which parts it has, what pushes what, and what it is for. Run a model forward, and it predicts what happens next. Most physicians held miasma, the idea that bad air causes disease, so the parts that mattered were the air and the windows. Semmelweis’s first model made posture the part that pushed, and his second made it the bell. Each predicted that changing its part would save mothers.
So Semmelweis tested each model the plain way: change one part alone and measure the gap. He asked for the posture change, and later the priest’s bell stopped. The count held both times, so neither part pushed anything. A mechanism is a what-pushes-what link that a test tried to break and could not.
Which part to try came from two old tools of thought. One is reasoning from what can be observed, not from what everyone assumes. Miasma was assumed, and it would have kept him checking windows. He observed two wards under one roof breathing the same air, and one lost more than twice as many mothers. Bad air could not explain the gap. The other is Occam’s razor: take the simplest account that fits everything observed, not the nearest one. It is named for William of Ockham, an English friar of the 1300s, yet its famous wording appears nowhere in his writings. Statisticians use this razor too: of two models that fit, keep the one with fewer assumptions. So does anyone who swaps a dead remote’s batteries before blaming the TV. One part fit the difference between the clinics: what the doctors’ hands carried from an autopsy to a delivery.
That mental model, something on poorly cleaned hands carried from a corpse to a mother, fills in all three: the parts, what pushes what, and what the clinic is for. The model passes the portable test: it holds on any ward, on any morning.
The same reading works on the morning walk. Its parts are a buzzing alarm, the shoes by the door, a bedtime, a dog, and a friend at the corner. “Not a morning person” is its mental model. The one week the walk held is its Second Clinic. Whatever was different that week is the part to change alone.
Semmelweis found his mechanism one part at a time. Convincing his colleagues was harder.
What the Basin Could Not Wash
Five of the twelve questions, numbered as in that list, ask what came next. Each is a question anyone could ask of their own work: how to be heard, what to want, who stands with them.
Question 7 asks how to make an idea ready to be received. He had the data. He published his table in 1861 (Figure 4) and wrote open letters to physicians across Europe. Many of them dismissed the idea. The women on their knees had known which ward to fear before any table did.
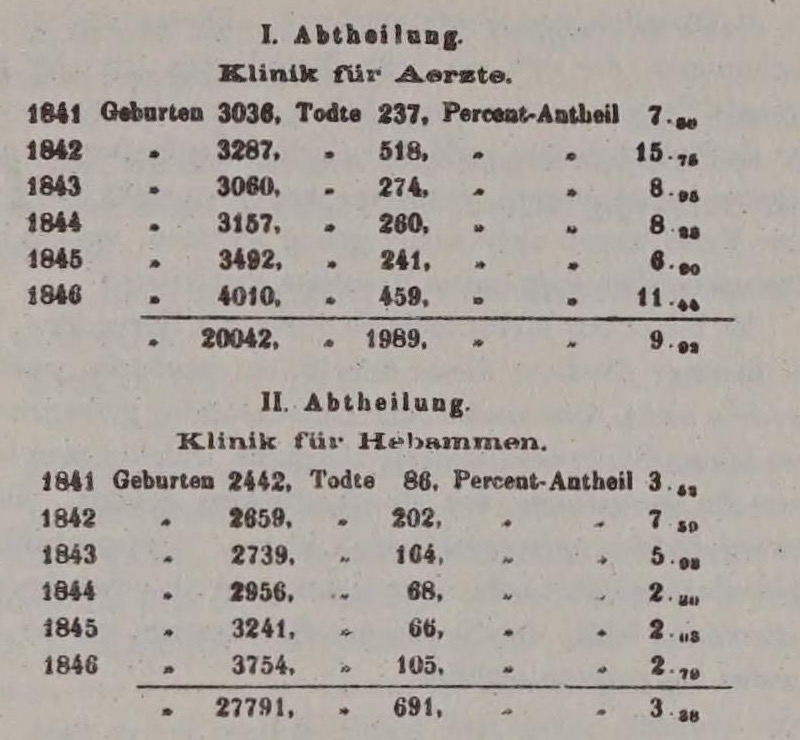
Figure 4. The table he published. Each row is one year before the chlorine, with births (Geburten) and deaths (Todte) in the doctors’ clinic (I. Abtheilung) and the midwives’ clinic (II. Abtheilung). Across the six years, 9.92 percent of mothers died in the doctors’ clinic. In the midwives’ clinic it was 3.88 percent. The printed midwife total of 27,791 births is a misprint. The six rows add to 17,791, my own recount. The printed 3.38 percent is a misprint too. Divided by the true total, the 691 deaths give the 3.88 above. From Semmelweis, Die Aetiologie, der Begriff und die Prophylaxis des Kindbettfiebers (1861), p. 305. Wellcome Collection scan via Internet Archive, Public Domain Mark; cropped.
On his own ward, he could give orders. By then he taught obstetrics, the medicine of childbirth, in Pest. On May 27, 1861, he had a notice printed for his students (Figure 5). Under a heavy black heading, in Hungarian, it orders them to wash their hands in the chlorine solution before and after every examination, until the hands turn slippery. A student who did not wash was barred from the course. The basin ruled his own ward, but never the men who ran the wards in Vienna.

Figure 5. His order to the students of the Pest obstetrics clinic, 1861. Public domain, via Wikimedia Commons.

Question 5 asks, given any problem, how to find the question worth answering. The first question, what was killing the mothers, he answered within months of Kolletschka’s death. A second one was harder: whether to convince Vienna’s medical leaders, or to run his own clinic well and let its counts do the persuading. By 1848 his doctors lost fewer mothers than the midwives did. His open letters challenged the European medical establishment.
Question 4 asks what the objective function is: the one quantity a person is really trying to make as large as possible. An objective function works like a cook’s goal. Two cooks can follow the same recipe, one aiming for the cheapest dinner and one for the fastest, and serve different meals from the same kitchen. One biography describes a man with no interest in academic recognition, fighting for the lives of new mothers. To Professor Späth he wrote, “And you, Herr Professor, have been a partner in this massacre.” One man maximizes saved mothers, another maximizes being believed, and Semmelweis’s letters alone cannot prove which he was.
Question 12 asks who his people are. Johann Klein, his superior, saw the death rate fall and gave the credit to a new ventilation system. Semmelweis pointed out that both clinics used the same ventilation. Klein kept to bad air anyway. He resented Semmelweis and the young doctors around him for their liberal views. In March 1849, when Semmelweis’s two-year post as assistant ran out, Klein did not renew it. The man above him was not one of his people (Figure 6).

Figure 6. The medical faculty of the university in Pest, 1863. Semmelweis stands fourth from left, arms crossed. Lithograph by József Marastoni, public domain, via Wikimedia Commons.

Question 11 asks what he owes the world, when he knows how to save mothers and the people in charge will not act. In July 1865 his mind failed. One account ties the decline to the constant criticism of his ideas, and the sources do not settle the cause. He was committed to a psychiatric institution near Vienna and died two weeks later, on August 13, of sepsis, an infection that spreads through the blood. It was the kind of infection his basin was meant to stop. Germ theory, the finding that living microbes such as bacteria cause infection, later explained what he had seen. The medical establishment accepted his findings only after his death.
Five questions, one life. Only some of them have moving parts.
Which Questions a Basin Can Answer
Klein clung to bad air as the deaths fell, and that grip has moving parts. What Semmelweis owed the world has none. A mechanism question asks about the first two of Meadows’s three things: a system’s parts, and what pushes what.
Question 12 is one. A person keeps a position until the evidence makes keeping it cost more standing than dropping it. That grip fits Klein, and any colleague whose name is on the wrong answer. It does not name Semmelweis’s people, but it predicts how the men above him would act once their own standing was at risk. Like posture before he changed it, the grip is a candidate, not a tested finding.
Question 7 is a mechanism question too: an idea spreads faster the more its messenger is trusted, and slower the more it threatens the people in charge.
Questions 4 and 11 are values questions. They ask about the third thing, what the whole is for: what a person ought to want, or what a person owes. A purpose is chosen, not watched, so no chain of causes answers it. A perfect model of how credit works in a medical hierarchy would still not tell Semmelweis whether to want credit or only saved mothers. Question 5 falls in between, part a pattern to describe and part a judgment of worth (Figure 7).

Figure 7. The five questions, sorted by what can answer them. Drawn for this piece.
Posture and fear felt as reasonable to Semmelweis as cadaverous particles did. From the inside, a guess and a mechanism feel the same. A guess becomes a cause only when changing it alone moves the outcome.
Why the morning walk dies by day fourteen is a mechanism question, one that changing one part at a time can answer. Whether that hour should go to walking or to sleep is a values question, and no week of watching settles it. Only deciding what the hour is for does. Treating the second like the first buys another month of evidence for a question evidence cannot close. The friend left waiting at the corner is the person to send this piece to.
The priest’s bell stopped, and the count did not improve. The doctors’ hands went into the basin, and the count fell.
A Closing Reflection. Posture and the bell stood for every guess that feels like a cause; the basin, for the change that moved the count. A recurring problem runs on a guess or a mechanism, and only a change made alone tells which.
- Name your bell. Right now, pick one health habit that keeps slipping, like the bedtime that drifts past midnight or the vitamins still in the drawer this morning. Say out loud, in one sentence, why you think it slips. Has anything ever tested that reason, or was it just the nearest one?
- Find your Second Clinic. At your desk tomorrow, pick one work problem that repeats, like the report that went out late again this month or last Monday’s meeting that ran over. Find one time it went right, or ask a coworker to name one. What was different then, and how many evenings has the guess about it cost you?
- Change one thing alone. Tomorrow morning, when the alarm goes off, change only the part you blame for the walk that dies by week two, like the route or the friend at the corner. If the walk outlasts week two, you found a cause. If not, is the question how things work, or what you want the hour for?
Somewhere in every recurring problem is a bell that changed nothing, and a basin waiting to be tried. The basin of chlorinated lime answered his first question, and the questions after it outlived him.
Be careful claiming causality: observing a problem shows you what comes with it, not what causes it. Change one thing alone, like a morning or bedtime routine, and watch. If nothing changes, the reason you blamed was only a guess.

Where This Practice Came From
Craik proposed in 1943 that the mind builds small working models of reality to test outcomes before acting. Forty years later the cognitive scientist Philip Johnson-Laird built a theory of reasoning on that idea. Cognitive scientists still argue over whether people reason by running such models or by following fixed rules, like the steps of a logic proof.
Intellectual Honesty Note. Reading the two clinics as one system with parts taken out, and the split into mechanism questions and values questions along Meadows’s three things, are my own framing, not Craik’s, Meadows’s or Ackoff’s. The two mechanisms in the last section, evidence against standing for Klein and trust against threat for an idea, are my readings, not findings from a study. Some readings of Semmelweis’s story are mine, not Johnston’s or Gombos’s: his posture and bell steps as tests of one part alone, the three differences in Figure 3, and the two tools of thought behind his choice. So are how reasonable posture and fear felt to him, and what his letters can prove about his aim. The morning walk is an invented example. The wording of the 1861 Pest notice in Figure 5 is my own reading of the Hungarian.
References
Ackoff, R. L. (2015, November 2). Systems thinking speech by Dr. Russell Ackoff [Video]. YouTube. https://www.youtube.com/watch?v=EbLh7rZ3rhU
Craik, K. J. W. (1943). The Nature of Explanation. Cambridge University Press.
Gombos, Róza. “Ignaz Semmelweis.” Science History Institute, September 15, 2025. https://www.sciencehistory.org/education/scientific-biographies/ignaz-semmelweis/
Johnson-Laird, P. N. (1983). Mental Models: Towards a Cognitive Science of Language, Inference, and Consciousness (No. 6). Harvard University Press.
Johnson-Laird, P. N. (2010). Mental models and human reasoning. Proceedings of the National Academy of Sciences, 107(43), 18243-18250. https://doi.org/10.1073/pnas.1012933107
Johnson-Laird, P. N., Girotto, V., & Legrenzi, P. (1998). Mental Models: a Gentle Guide for Outsiders. Sistemi intelligenti, 9(68), 33.
Johnston, Katrina. “Ignaz Semmelweis: The Saviour of Mothers.” Canadian Museum of Health Care, 2022. https://www.museumofhealthcare.ca/blog/ignaz-semmelweis-the-saviour-of-mothers
Meadows, D. H. (2008). Thinking in systems: A primer (D. Wright, Ed.). Chelsea Green.
Semmelweis, I. P. (1861). Die Aetiologie, der Begriff und die Prophylaxis des Kindbettfiebers. C. A. Hartleben.
Spade, P. V., Panaccio, C., & Pelletier, J. (2024). “William of Ockham.” The Stanford Encyclopedia of Philosophy, Spring 2024 edition. https://plato.stanford.edu/entries/ockham/
University of Vienna. (n.d.). History of the campus. https://www.univie.ac.at/en/about-us/opening-hours-and-locations/campus/history-of-the-campus